
Why a Future Knee Replacement Recommendation Can Double a New York Tibial Plateau Fracture Verdict — If Your Surgeon Says It Right

Updated: Nov 12
Updated October 27, 2026
A box truck runs the light at East Tremont and Southern Boulevard in the Bronx and slams into your driver's side. The dashboard collapses into your leg, and the top of your shinbone shatters where it meets the knee joint. The diagnosis is a tibial plateau fracture, and the surgeon at St. Barnabas rebuilds it with a plate and screws. Months later, you're walking again, but your orthopedist warns you that the joint surface will never be smooth, and arthritis is coming. Whether that warning turns into a vague chart note or a sworn, specific recommendation for a future knee replacement can change what a jury is allowed to hear about your future.
Key takeaways
A tibial plateau fracture damages the knee's joint surface, and post-traumatic arthritis can later lead to a total knee replacement.
New York allows recovery for a future surgery only when a doctor says it is needed with a reasonable degree of medical certainty.
Words like "may" or "possible" in your chart let the defense argue the future surgery should never reach the jury.
Your treating orthopedist's records should state the knee replacement opinion clearly, with a timeframe, long before expert disclosures are exchanged.
You don't have to undergo the knee replacement before trial to claim its cost if the need is properly documented.
What Makes a Tibial Plateau Fracture Different From Other Broken Legs?
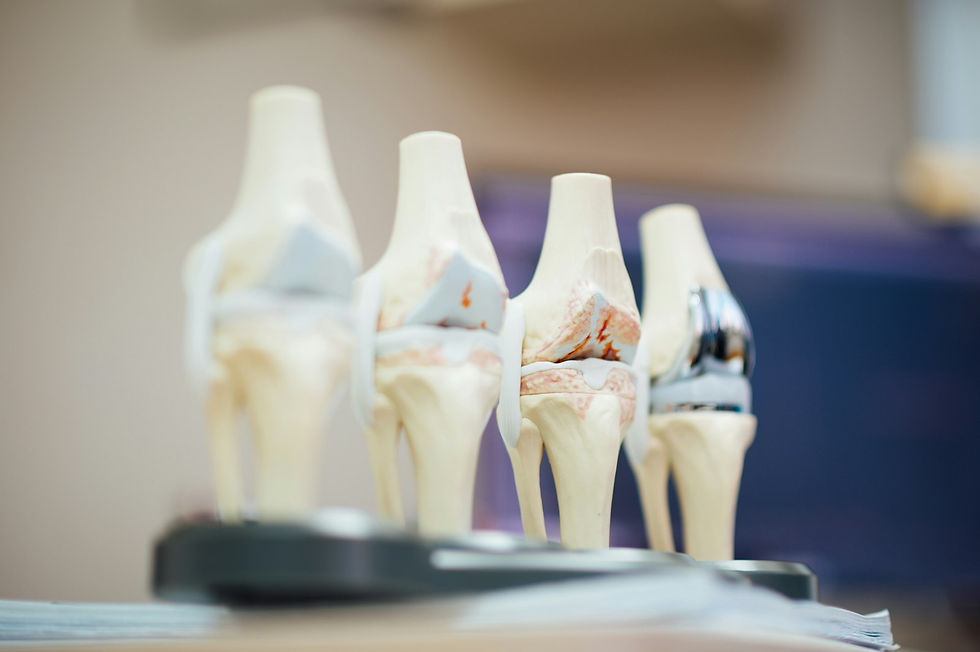
A tibial plateau fracture is a break through the weight-bearing surface of your knee joint, not just the shaft of a bone, and that's exactly why it carries long-term consequences that an ordinary leg fracture doesn't. The tibial plateau is the flat top of your shinbone where the cartilage of your femur glides with every step. When a crash or a fall drives the femur down into that surface like a hammer into drywall, the bone doesn't just crack. It depresses, splits, and leaves the joint surface uneven even after a skilled surgeon performs open reduction and internal fixation (the operation where the fragments are screwed back together under a metal plate).
An uneven joint surface grinds. Grinding wears away cartilage. Worn cartilage becomes post-traumatic arthritis, which is osteoarthritis caused by an injury rather than by age. Research published in the Journal of Orthopaedic Trauma indicates that post-traumatic arthritis accounts for a significant share of symptomatic osteoarthritis in the United States, and joint-surface fractures like the tibial plateau are among the classic causes. The CDC reports that osteoarthritis is the most common form of arthritis among American adults, and once it takes hold in a reconstructed knee, there's no reversing it.
That's why the endgame for many tibial plateau fracture patients (especially those with depressed or comminuted fractures) is a total knee replacement, where the damaged joint surfaces are removed and replaced with metal and plastic components. The Mayo Clinic describes knee replacement as the standard treatment when arthritis pain no longer responds to conservative care. For a jury, the difference between "he broke his leg and it healed" and "she will need her knee cut out and replaced, possibly twice" is enormous. The same dynamic appears in acetabular fracture cases where a future hip replacement drives the value, where the future joint replacement often becomes the central issue in the damages case.
What Does "Reasonable Degree of Medical Certainty" Mean for Future Surgery Damages in New York?
In New York, you can recover money today for a surgery you haven't had yet, but only if a physician testifies that you will need it with a reasonable degree of medical certainty. That phrase is the legal standard courts apply to opinions about future medical treatment. In plain terms, it means the doctor must say the future knee replacement is more likely than not going to happen, based on your specific injury, your imaging, and the known natural course of post-traumatic arthritis. The doctor doesn't need to guarantee it. Medicine doesn't work in guarantees. But the opinion has to be a professional judgment about probability, not a guess about possibility.
Here's where tibial plateau fracture cases often turn. "This patient may develop arthritis and could someday need a knee replacement" is speculation. New York judges can strike that testimony, and defense lawyers will move to keep the future surgery away from the jury entirely. "Given the 8-millimeter depression of the lateral plateau, the post-traumatic arthritic changes already visible on X-ray, and this patient's age, it is my opinion with a reasonable degree of medical certainty that she will require a total knee replacement within 10 to 15 years" is the kind of specific, supported opinion courts look for. Same patient, same knee, completely different case.
You don't have to actually undergo the knee replacement before trial to recover its full cost. New York law lets you recover for a future surgery that's reasonably certain even if you choose to put it off for years, which matters because surgeons routinely tell younger patients to delay the operation as long as possible. We explained how this plays out with shoulders and knees in our post on surgery that's been recommended but not yet performed, and the same logic applies when the recommended procedure is a joint replacement.
Why Must the Knee Replacement Recommendation Appear in Your Treating Orthopedist's Records Before Trial?
Because a future surgery opinion that first appears at trial, from a paid expert who never treated you, looks manufactured, while the same opinion written into your treating surgeon's chart two years earlier looks like medicine. Juries in the Bronx and across New York instinctively trust the doctor who opened your leg, saw the shattered joint surface with their own eyes, and followed you through every post-op visit. That credibility advantage is the entire theme of our post comparing treating surgeon testimony against the defense IME doctor, and it's never stronger than on the question of future surgery.
The practical problem is that busy orthopedists don't naturally write litigation-ready chart notes. They write "doing well, continue PT, follow up PRN." If your surgeon genuinely believes you're headed for a knee replacement, that belief needs to live in the medical records long before anyone exchanges expert disclosures. Under CPLR § 3101(d), upon request, each side must identify the experts it expects to call at trial and disclose in reasonable detail the subject matter and substance of their expected opinions. When your disclosure says the treating orthopedist will testify to a future knee replacement, the defense immediately pulls the chart to see whether that opinion appears anywhere in the actual treatment records. If it doesn't, their cross-examination writes itself: "Doctor, in 14 office visits over three years, you never once documented that this patient needs a knee replacement — the first time that opinion appears anywhere is after the lawyers got involved, correct?"
That cross-examination is not the only risk. In Gjeka v. Iron Horse Transp., Inc., 191 A.D.3d 526 (App. Div. 1st Dep't 2021), the First Department, whose decisions bind Bronx courts, vacated an award for future medical expenses because "Plaintiff failed to serve a CPLR 3101(d)(1)(i) expert disclosure notifying defendants that his treating physician would testify to his future medical needs and associated expenses, and defendants had no other notice of this testimony." The court also found that the doctor's testimony, given without a report, was not enough to prove the award with reasonable certainty.
A well-documented chart avoids that trap. The strongest records typically include a few specific elements:
Serial X-rays or MRIs showing progressive joint-space narrowing — objective proof the arthritis is advancing, not a prediction
Documented failed conservative care: physical therapy, bracing, cortisone or gel injections that no longer control pain
A dated note stating the surgeon's opinion that a total knee replacement will be necessary, with a timeframe
Notation of the patient's age and the likelihood of revision surgery down the road
That last point deserves emphasis. The Mayo Clinic notes that knee implants wear out — most last well over a decade, but not forever. If you're 38 years old when a Bronx crash destroys your tibial plateau, a knee replacement at 50 likely means a revision surgery at 65 or 70. Revision surgeries are longer, riskier, and more expensive than the first replacement. A life care plan that captures one replacement plus one revision, with the associated rehab, puts both procedures into the future medical costs the jury considers, separate from pain and suffering. It's the same compounding effect we described in spine cases involving adjacent segment disease and the second fusion — the first surgery plants the seed for the next one, and honest medicine requires pricing them all.
How Does Defense Counsel Exploit a Vague "May Need Surgery Someday" Chart Note?
A vague chart note gives the defense two weapons at once: a motion to preclude the future surgery claim before trial, and devastating cross-examination material if the claim survives. Insurance defense lawyers read every page of your medical records hunting for soft language. "Patient may be a candidate for TKR in the future." "Possible arthroplasty down the road." "Will monitor for arthritic changes." Each of those phrases sounds harmless when a doctor dictates it, and each one is a gift to the defense.
First comes the pretrial motion. Defense counsel argues that an opinion phrased as "may" or "possible" doesn't meet the reasonable-certainty standard, so the jury should never hear about a knee replacement at all. If the judge agrees, the single most valuable component of your damages vanishes before opening statements. Second, even if your expert testifies to certainty at trial, the defense confronts the treating surgeon with their own words: "You wrote 'may,' Doctor. 'May' means it also may not, true?" Then the defense IME doctor (the physician the insurance company hired to examine you once for 15 minutes) takes the stand and testifies that your knee shows only "mild degenerative changes consistent with age" and that no replacement is indicated. We broke down how juries weigh that contest in our post on the treating physician versus the hired defense expert.
A second defense move blindsides unrepresented claimants: when the arthritis finally shows up on X-ray, the IME doctor reclassifies it as "preexisting degeneration" unrelated to the fracture, which is why your lawyer secures the emergency room imaging from the day of the crash, showing a joint that was arthritis-free until the truck hit you. That before-and-after imaging comparison, explained by the National Institute of Arthritis and Musculoskeletal and Skin Diseases framework of how osteoarthritis develops and progresses, converts the causation fight from a swearing contest into a timeline the jury can see with their own eyes. Tibial plateau fractures have a related hidden-injury problem too — they're sometimes missed entirely on initial films, a trap we covered in our post on the unhappy triad and the hidden tibial plateau fracture.
How Do You Actually Prove the Cost of a Future Knee Replacement to a New York Jury?
You prove it with a chain of three witnesses: the treating orthopedist who establishes medical necessity, a life care planner who itemizes every future expense, and often an economist who converts those costs into present-day dollars. The surgeon supplies the "whether" and the "when." The life care planner (usually a rehabilitation nurse or physician who specializes in projecting lifetime medical needs) supplies the "how much," pricing the hospital stay, the surgeon's and anesthesiologist's fees, the implant hardware, months of physical therapy, assistive devices, and the eventual revision. In the New York metropolitan area, it isn't unusual for a single total knee replacement episode, from pre-surgical clearance through completed rehab, to be projected at $70,000 to $100,000 in a life care plan, with a revision priced even higher. Each of those costs needs its own proof. In Leto v. Amrex Chemical Co., 85 A.D.3d 1509 (App. Div. 3d Dep't 2011), the court vacated a future medical expense award because there was no evidence of what the expected future tests and medications would cost, and past expenses could not simply be projected forward to fill the gap.
The jury never hears whether your health insurance might pick up some of those costs. New York handles that issue after the verdict: under CPLR § 4545, the court (not the jury) reduces the economic portion of a personal injury award (such as medical costs) by amounts that collateral sources like insurance will replace with reasonable certainty, subject to the statute's conditions. Your trial presentation stays focused on the full, real cost of the medicine you'll need.
Beyond the economic numbers, the future surgery recommendation transforms your pain-and-suffering claim. A plaintiff whose fracture "healed" argues about past pain. A plaintiff facing a knee replacement argues about a future: the years of grinding pain while waiting to be "old enough" for the implant, another hospitalization, another rehab, activity restrictions for life, and the knowledge that the artificial joint will wear out too. That's the permanency story juries are asked to weigh when they consider future pain and suffering, and it's why the defense fights so hard to keep the future surgery out. Don't let them shrink the injury the way they do with biomechanical experts in low-impact crash cases — the answer in both situations is objective medical proof, documented early and stated with certainty.
Most cases should settle, especially given how long New York cases take, and taking a little less now can be worth more than waiting years. But some cases are worth more than an insurer will pay without a trial, and those clients need to be ready for a long fight.
Frequently Asked Questions
Do I have to get the knee replacement before my tibial plateau fracture case settles or goes to trial?
No. New York lets you recover the cost of a future surgery that a physician says you'll need with a reasonable degree of medical certainty, even if you haven't scheduled it. Many surgeons tell younger patients to delay the replacement as long as possible, and that delay doesn't reduce your recovery if the need is properly documented.
What if my orthopedist says I'm too young for a knee replacement right now?
That's common, and it doesn't undercut a claim for the future surgery. Being 'too young' means living with arthritic pain for years while waiting for the surgery, and it often means the implant will wear out during your lifetime, requiring a revision surgery. Both the waiting period and the revision belong in your damages claim.
Can the insurance company make me see their own doctor about my knee?
Yes. In a New York lawsuit, the defense is entitled to have you examined by a physician it selects, often called an IME. That doctor will likely minimize your arthritis or call it age-related, which is why your attorney prepares you for the exam and counters it with your treating surgeon's records and serial imaging.
How much does a future knee replacement recommendation add to a tibial plateau fracture settlement?
It depends on your age, liability, and documentation. A properly proven future knee replacement allows the jury to consider the projected surgical and rehab costs, which life care plans in the New York area often put at $70,000 to $100,000 or more per procedure, along with pain and suffering for the permanency of the injury. The cost of each procedure needs its own proof, not just a doctor's statement that surgery is coming.
Conclusion
A tibial plateau fracture isn't just a broken leg — it's joint-surface damage that frequently ends in a total knee replacement, and New York law allows recovery today for that future surgery if your treating orthopedist documents it with a reasonable degree of medical certainty. A vague "may need surgery someday" note invites the defense to keep the future surgery away from the jury, while a specific, well-supported recommendation in the chart gives the jury a clear medical basis to consider it. Getting that recommendation into the chart is one step; for the rest of a knee fracture case, see how Yassi Law PC handles serious injury cases.
If you or someone you know suffered a tibial plateau fracture or faces a future knee replacement because of someone else's negligence, Reza Yassi at Yassi Law PC is ready to help. Call us today at 646-992-2138 for a consultation.
Written by Reza Yassi
Prior results do not guarantee a similar outcome.
This article is for informational purposes only and does not constitute legal advice. Although I am an attorney, I am not your attorney, and reading this article does not create an attorney-client relationship. Laws vary by jurisdiction and may have changed since the publication of this article. For advice specific to your situation, consult a qualified attorney.

